

Retatrutide is emerging as one of the most promising new drugs in metabolic health. In contrast to established GLP-1 receptor agonists such as Semaglutide (marketed as Wegovy and Ozempic) or dual-acting agents like Tirzepatide, Retatrutide is designed as a triple agonist that simultaneously activates GLP-1, GIP, and glucagon receptors. This combined receptor activity has produced remarkable outcomes in early human studies, where participants achieved average body weight reductions exceeding 24% within roughly a year at the highest tested doses.
Due to its high potency, the Retatrutide dosing schedule needs to be well understood, so that clinicians can assess the proper dosage based on efficacy and tolerability. Examining the dosing framework used in current clinical trials helps clarify how future clinical use and regulatory recommendations might evolve once the medication receives FDA authorization.
In this guide, you will find:
- The dose ranges evaluated so far (1–12 mg weekly)
- How gradual titration influences outcomes and side-effect management
- Key distinctions between Retatrutide and other GLP-1/GIP agonists
- What upcoming data may suggest about its clinical and real-world potential
Key Takeaways
- Retatrutide is an investigational triple-agonist medication that activates GLP-1, GIP, and glucagon receptors to improve metabolism and reduce appetite.
- Clinical trials have tested weekly doses ranging from 1 mg to 12 mg, with gradual titration used to improve tolerability and minimize gastrointestinal side effects.
- Higher doses of retatrutide produced significant weight loss, with Phase 2 trials reporting average reductions of about 24% of body weight after 48 weeks.
- The medication may improve multiple metabolic markers, including blood glucose control, insulin sensitivity, blood pressure, and lipid profiles.
- Retatrutide remains under clinical investigation and has not yet received regulatory approval, with ongoing Phase 3 trials evaluating long-term safety and effectiveness.
What Is Retatrutide and How Does It Work?
Retatrutide is a once-weekly subcutaneous investigational medication developed by Eli Lilly for the treatment of obesity and type 2 diabetes. It is a novel triple agonist that simultaneously targets the glucagon-like peptide-1 (GLP-1), glucose-dependent insulinotropic polypeptide (GIP), and glucagon receptors. This mechanism is distinct from currently approved medications such as semaglutide and tirzepatide, which act as dual agonists. By stimulating these three pathways, retatrutide enhances glucose metabolism, suppresses appetite, and increases energy expenditure. [1]
At the cellular level, GLP-1 and GIP receptor activation enhances insulin secretion and slows gastric emptying, contributing to reduced caloric intake and improved glycemic control. Concurrent glucagon receptor activation promotes lipolysis and thermogenesis, leading to reductions in adipose tissue. Collectively, these mechanisms position retatrutide as a promising multi-pathway therapeutic candidate in obesity management and metabolic regulation. [1]
Clinical investigations have yielded highly promising outcomes. In Phase 2 trials, individuals receiving higher doses of Retatrutide experienced body weight reductions averaging up to 24% within a 48-week period. Beyond its impact on weight, the therapy also demonstrated significant improvements in several metabolic parameters, including glucose regulation, hemoglobin A1c, blood pressure, and overall insulin responsiveness. In a clinical setting, it is delivered through a once-weekly subcutaneous injection. The compound has not yet received regulatory approval and remains under evaluation in Phase 3 studies, which aim to determine its long-term safety profile, durability of weight reduction, and extended metabolic effects. [1]
Understanding the Retatrutide Dosing Schedule
The retatrutide dosing schedule follows a carefully designed titration process aimed at balancing efficacy and tolerability. Similar to other incretin-based drugs, retatrutide is administered via a once-weekly subcutaneous injection. The dosing strategy is built around a stepwise escalation model that allows the body to gradually adapt to gastrointestinal and metabolic effects, minimizing side effects such as nausea or vomiting. Many researchers use a Retatrutide dosage calculator to help estimate peptide concentrations and weekly dosing measurements during this adjustment phase.
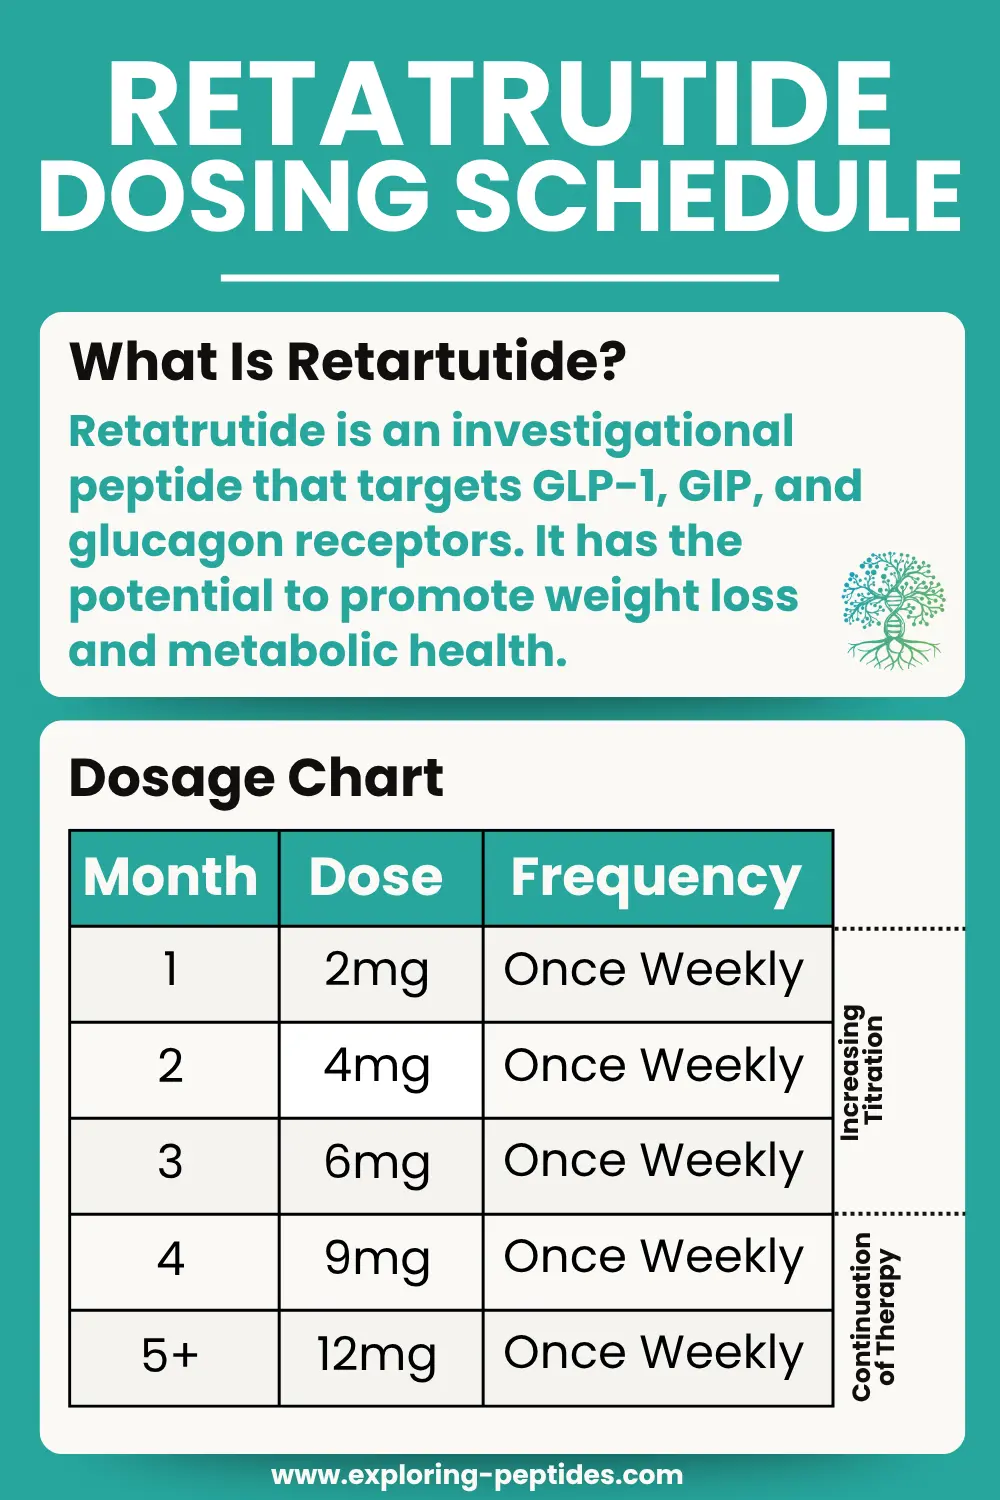
In early clinical trials, participants began with a starting dose of 2 mg per week, which was progressively increased over several weeks until reaching higher doses that demonstrated maximal therapeutic benefit. This gradual titration schedule was a critical factor in achieving high adherence and favorable tolerability across different study populations. [2]
Clinical Trials Doses
Across multiple clinical trials, retatrutide was evaluated in varying doses to determine optimal therapeutic windows for both weight loss and glycemic control. The phase 2 studies employed a range of 1 mg to 12 mg weekly doses, with most participants reaching target doses within 24 to 36 weeks. [1] [2]
- 1 mg per week – The lowest tested dose, primarily intended to evaluate tolerability and establish baseline safety. This level produced only minimal weight loss effects.
- 4 mg per week – Represented a mid-range dose that achieved greater weight reduction compared to 1 mg but remained below the most effective outcomes.
- 8 mg per week – Resulted in substantial body weight decreases, suggesting it may offer an optimal balance between efficacy and tolerability.
- 12 mg per week – The maximum dose studied, associated with the most pronounced reductions in body weight, with some participants experiencing losses exceeding 24% over a 48-week period.
Comparing Retatrutide Doses and Titration Phases
The titration schedule in retatrutide studies followed a gradual dose-based approach, typically involving dose increases every four weeks. For example, a participant might receive 2 mg in weeks 1–4, 4 mg in weeks 5 to 8, 8 mg in weeks 9 to 12, and finally 12 mg from week 13 onward as a maintenance dose. This stepwise escalation minimized gastrointestinal side effects and optimized long-term adherence. [1]
The structured progression was essential for balancing metabolic benefits with patient tolerability. Participants who experienced adverse reactions could remain on a lower dose for an extended period before advancing, ensuring personalized therapy management.
In Phase 2 research reported in The New England Journal of Medicine, participants began treatment with a low introductory dose, typically between 2 and 4 mg per week, and gradually increased to target doses ranging from 8 to 12 mg over several weeks. This stepwise dosing approach was designed to minimize gastrointestinal symptoms (nausea, vomiting, and diarrhea) and help clinicians distinguish between the levels at which the drug remains tolerable and those that maximize therapeutic benefit. It also provided a gradual adjustment to the medication’s triple agonist mechanism, preventing excessive hormonal stimulation early in treatment. [1]
Dosing for Weight Loss VS. Diabetes
Retatrutide has been evaluated in clinical studies involving both adults with obesity but no diabetes and individuals diagnosed with type 2 diabetes, revealing distinct patterns in how dosing influences outcomes within each group.
In obese individuals without diabetes, weekly doses between 8 to 12 mg produced substantial reductions in body weight, often surpassing those observed with semaglutide or tirzepatide. In contrast, diabetic participants typically responded well to intermediate doses (4–8 mg weekly), which balanced weight loss with glucose management and minimized hypoglycemia risk.
Weight Loss in Obese Adults
In a 48-week phase 2 trial published in The New England Journal of Medicine, retatrutide demonstrated unprecedented weight loss efficacy in adults with obesity. Participants receiving 12 mg per week achieved an average reduction of 24.2% in body weight, compared to 2.1% in the placebo group. Even at moderate doses, retatrutide outperformed existing incretin mimetics, with 8 mg weekly doses yielding reductions exceeding 20%. [1] [3]
These results support the hypothesis that multi-receptor agonism exerts synergistic effects on energy balance and adiposity. The magnitude of weight loss observed suggests retatrutide may represent a new benchmark in anti-obesity therapy pending FDA approval.
Impact on Type 2 Diabetes
For participants with type 2 diabetes, retatrutide significantly improved glycemic parameters. Trials demonstrated marked reductions in HbA1c and fasting glucose levels, along with improvements in insulin sensitivity and beta-cell responsiveness. Notably, higher doses provided greater glucose-lowering efficacy but required careful monitoring for gastrointestinal side effects. [3]
The combination of potent weight loss and glucose control underscores retatrutide’s potential as a dual-purpose treatment for metabolic disorders, addressing both adiposity and insulin resistance in a single medication.
Retatrutide Dosing Schedule Chart
| Week Range | Weekly Dose | Notes on Titration & Tolerability |
|---|---|---|
| Weeks 1 – 4 | 2 – 4 mg | This initial dose is intended to reduce nausea and gastrointestinal discomfort, giving the body time to adjust. |
| Weeks 5 – 8 | 4 – 8 mg |
This mid-range dose marks the point where more pronounced weight loss is observed, though gastrointestinal side effects may also reach their highest intensity. |
| Weeks 9 – 12 | 8 mg | This dose is viewed as therapeutically effective, producing meaningful weight loss while maintaining a generally tolerable side-effect profile. |
| Weeks 13+ | 12 mg | The highest dose studied led to the largest weight loss, around 24 percent over 48 weeks, but was also linked to an increased risk of gastrointestinal side effects. |
Retartrutide VS. Semaglutide
Semaglutide, sold as Wegovy and Ozempic, is a GLP-1 receptor agonist widely used for obesity and metabolic health. Its dosing typically begins at 0.25 mg weekly and is titrated up to 2.4 mg weekly. Retatrutide, in contrast, has been tested at doses up to 12 mg per week. However, its superior efficacy is not simply due to higher dosing.
Retatrutide’s triple agonist activity, targeting GLP-1, GIP, and glucagon receptors, enhances both weight loss and metabolic improvements beyond what is typically observed with GLP-1-only therapy. Early clinical trials show that Retatrutide produces greater average body weight reductions while offering comparable improvements in glycemic control. Despite these promising results, Semaglutide benefits from long-term approval and well-established safety data.
Read more about Retartutide vs Semaglutide
Retartutide VS. Tirzepatide
Tirzepatide acts as a dual GLP-1/GIP receptor agonist, with dosing starting at 2.5 mg weekly and titrating to 15 mg weekly. While Tirzepatide produces impressive weight loss (up to about 21% at the highest dose), Retatrutide’s addition of glucagon receptor activation may further enhance fat metabolism, thermogenesis, and overall metabolic outcomes. Early studies suggest that Retatrutide could achieve greater weight reduction and broader metabolic benefits at lower relative exposure compared with Tirzepatide, although phase 3 trials are ongoing to confirm these findings.
Clinical Study Results and Key Findings
Aggregated results across clinical trials confirm that retatrutide produces profound weight loss and metabolic improvements with a manageable safety profile. Dose-dependent effects were consistently observed, with greater doses correlating to higher efficacy. Importantly, long-term data indicate sustained benefits without significant rebound weight gain post-treatment.
Safety and Side Effects At Different Retartutide Doses
Like other therapies that target incretin pathways, Retatrutide’s side effects are closely linked to both the dose and how quickly it is escalated. Higher doses tend to provide the greatest weight loss and metabolic improvements, but are also associated with an increased likelihood and intensity of gastrointestinal symptoms.
Commonly Reported Side Effects
The most frequently observed adverse events in the Phase 2 trial were gastrointestinal in nature, including nausea, vomiting, diarrhea, and constipation. These events were generally mild to moderate, occurred predominantly during dose escalation, and often decreased in frequency or intensity as participants adapted to the target dose.
Other reported effects included:
- Transient fatigue
- Reduced appetite (therapeutically desirable in the context of weight loss)
- Mild injection-site reactions
- Altered skin sensations or cutaneous hyperesthesia (reported in ~7% of participants, mild and non-serious)
Serious adverse events were rare and occurred at similar rates in the retatrutide and placebo groups (approximately 4%). These included isolated cases of pancreatitis, prolonged QT syndrome (associated with concomitant medications), and transient elevations in liver enzymes. Importantly, no participants experienced clinically significant hypoglycemia, medullary thyroid cancer, or C-cell hyperplasia, consistent with the known safety profile of incretin therapies. [1]
Safety Monitoring
Retatrutide requires careful monitoring, especially during dose escalation, to ensure early identification and management of adverse effects. Clinical monitoring should include:
- Periodic assessment of liver enzymes (ALT, AST) to detect transient increases. Elevations were uncommon (1% of participants) and generally resolved without intervention.
- Pancreatic enzyme evaluation (amylase and lipase), particularly for individuals with predisposing conditions, since mild asymptomatic increases were occasionally observed.
- Cardiovascular monitoring, as dose-dependent increases in heart rate were noted, peaking around 24 weeks and declining thereafter.
- Gallbladder and biliary system assessment, given the potential risk for gallbladder disease associated with incretin therapies. [1]
Importance of Titration
Gradual dose escalation is critical to balancing efficacy and tolerability. In the Phase 2 trial, starting at a lower dose (2 mg versus 4 mg) significantly reduced the incidence and severity of gastrointestinal adverse events without compromising weight-loss outcomes. Careful titration allows participants’ gastrointestinal systems to adapt and minimizes the likelihood of treatment discontinuation due to adverse effects.
As with other incretin mimetics, retatrutide requires careful monitoring during dose escalation. Physicians are advised to evaluate liver and pancreatic enzymes periodically and monitor for signs of gallbladder disease. Individuals with a history of medullary thyroid carcinoma or multiple endocrine neoplasia type 2 (MEN2) are contraindicated due to mechanistic overlap with GLP-1 agonists. [1]
Final Thoughts on Retatrutide Dosing and Effectiveness
Retatrutide represents a significant advancement in metabolic therapy, offering a potentially highly effective approach to weight loss and glycemic control. Through precise dose optimization, gradual titration, and individualized management, it has demonstrated superior outcomes in both obesity and type 2 diabetes populations.
While long-term safety and cardiovascular outcome data remain under investigation, current clinical results position retatrutide as a potential paradigm shift among next-generation incretin-based medications. As additional FDA submissions and real-world studies emerge, further clarification of optimal dosing strategies and sustained efficacy will shape its role in future metabolic treatment protocols.
FAQs
What Is The Typical Retatrutide Dosing Schedule In Clinical Trials?
In clinical trials, retatrutide was generally introduced with a low starting dose and increased gradually over time. Most study protocols used once-weekly subcutaneous injections with step-up titration every few weeks to improve tolerability. The goal was to help participants adjust before reaching higher maintenance doses associated with stronger weight loss effects.
What Is The Starting Dose Of Retatrutide?
The starting dose in trials was usually low, often around 1 mg to 2 mg weekly, depending on the study design. A lower starting dose helps reduce the risk of gastrointestinal side effects such as nausea, vomiting, and diarrhea during the early weeks of treatment.
How Often Is Retatrutide Taken?
Retatrutide has been studied as a once-weekly injection. This weekly schedule is similar to other incretin-based medications used for obesity and metabolic health, making it more convenient than medications that require daily dosing.
Why Is Retatrutide Dose Titration Important?
Dose titration is important because retatrutide can cause gastrointestinal side effects, especially when doses are increased too quickly. A gradual escalation schedule gives the body time to adapt, which may improve tolerability, reduce treatment dropouts, and support better long-term adherence.
What Retatrutide Dose Produced The Most Weight Loss In Studies?
In Phase 2 obesity trials, the highest studied doses, particularly 12 mg weekly, produced the largest average body weight reductions. Participants at these doses experienced the strongest results, although higher doses were also more likely to cause gastrointestinal side effects during titration.
How Much Weight Loss Has Retatrutide Shown In Clinical Trials?
Clinical trials reported substantial, dose-dependent weight loss, with the highest-dose groups showing average reductions of around 24% of body weight at 48 weeks. Lower doses still produced meaningful results, but the greatest reductions were seen at the upper end of the dosing range.
Is Retatrutide Approved By The FDA?
No, retatrutide is still investigational and has not yet received FDA approval. It is currently being studied in ongoing clinical trials to better understand its long-term safety, effectiveness, and potential role in obesity and type 2 diabetes treatment.
Is Retatrutide Used For Weight Loss Or Diabetes?
Retatrutide is being studied for both obesity and type 2 diabetes. Research suggests it may support significant weight loss while also improving blood sugar control, insulin sensitivity, and other metabolic markers, which is why it is being closely watched as a potential dual-purpose therapy.
How Is Retatrutide Different From Semaglutide?
Semaglutide mainly targets the GLP-1 receptor, while retatrutide is a triple agonist that targets GLP-1, GIP, and glucagon receptors. This broader mechanism may explain why retatrutide has shown especially strong weight loss results in early trials, though semaglutide currently has the advantage of regulatory approval and longer-term real-world data.
How Is Retatrutide Different From Tirzepatide?
Tirzepatide targets GLP-1 and GIP receptors, while retatrutide adds glucagon receptor activation to that mechanism. This extra receptor activity may help increase energy expenditure and fat metabolism, which is one reason retatrutide is being studied as a possible next step beyond dual agonist therapies.
What Are The Most Common Side Effects Of Retatrutide?
The most common side effects reported in clinical trials were nausea, vomiting, diarrhea, constipation, and reduced appetite. These symptoms were usually most noticeable during dose escalation and often became more manageable as treatment continued.
Are Higher Retatrutide Doses More Effective?
Yes, available study data suggest that higher doses generally produced greater weight loss and stronger metabolic improvements. However, they also increased the likelihood of side effects, which is why careful titration and monitoring are important in clinical settings.
How Long Does It Take To See Results With Retatrutide?
Some metabolic effects may begin earlier, but the most meaningful weight loss results in trials developed over several months, especially as participants progressed through dose escalation and reached higher maintenance doses. The strongest published weight loss outcomes were reported at 48 weeks.
Can Retatrutide Cause Nausea?
Yes, nausea is one of the most commonly reported side effects of retatrutide. It is most often seen during the early stages of treatment or after dose increases, which is why gradual titration is a central part of the dosing strategy used in clinical studies.
Who May Need Extra Monitoring While Using Retatrutide?
People with a history of pancreatic issues, gallbladder problems, liver enzyme abnormalities, or certain endocrine cancer risks may need closer monitoring. Clinical supervision is especially important during dose escalation because side effects and tolerability can vary from person to person.
Is There A Standard Retatrutide Maintenance Dose Yet?
No, there is not yet an official standard maintenance dose because retatrutide remains under investigation. Trial data suggest that 8 mg and 12 mg weekly are among the most effective studied maintenance ranges, but future regulatory guidance will determine how it may eventually be prescribed.
Can Retatrutide Be Used In Real-World Weight Loss Programs Yet?
Not as an approved prescription medication at this time. Since retatrutide is still being evaluated in clinical trials, real-world use remains limited until regulatory agencies review the full safety and efficacy data and decide whether to authorize it.
Does Retatrutide Affect More Than Body Weight?
Yes, retatrutide has shown potential benefits beyond weight reduction. Clinical data suggest it may also improve blood glucose levels, HbA1c, insulin sensitivity, blood pressure, and lipid-related markers, making it a broader metabolic therapy candidate rather than a weight-loss-only drug.
[1] Jastreboff, A. M., Kaplan, L. M., Frías, J. P., Wu, Q., Du, Y., Gurbuz, S., Coskun, T., Haupt, A., Milicevic, Z., & Hartman, M. L., (2023). Triple–hormone-receptor agonist retatrutide for obesity — A phase 2 trial. New England Journal of Medicine, 389(6), 514–526. https://doi.org/10.1056/NEJMoa2301972
[2] Rosenstock, J., Frias, J., Jastreboff, A. M., Du, Y., Lou, J., Gurbuz, S., Thomas, M. K., Hartman, M. L., Haupt, A., Milicevic, Z., & Coskun, T. (2023). Retatrutide, a GIP, GLP‑1 and glucagon receptor agonist, for people with type 2 diabetes: A randomised, double‑blind, placebo and active‑controlled, parallel‑group, phase 2 trial conducted in the USA. The Lancet, 402(10401), 529–544.
[3] Pasqualotto, E., Ferreira, R. O. M., Chavez, M. P., Hohl, A., Ronsoni, M. F., Pasqualotto, T., de Moraes, F. C. A., Hespanhol, L., Watanabe, J. M. F., Lütkemeyer, C., & van de Sande-Lee, S. (2023). Effects of once-weekly subcutaneous retatrutide on weight and metabolic markers: A systematic review and meta-analysis of randomized controlled trials.



